Sunday, May 12, 2019

Mom with PKD needs Kidney, New PKD Research Strategy, Imaging PKD, Kidney Failure Symptoms

PKD Research

From Yale News, By Ziba Kashef

New strategy for untreatable kidney disease: targeting cell energy


The best hope for people with an inherited form of kidney disease that causes kidney failure is dialysis or a kidney transplant. But a study led by Yale researchers reveals a potential strategy for developing new drug therapies for these patients.

Senior author Barbara Ehrlich and her team used mouse models and human tissue samples to study one of the two mutated genes that lead to autosomal dominant polycystic kidney disease (ADPKD). This form of kidney disease is the most commonly inherited type and difficult to treat. The researchers focused their investigation on measuring the production of energy in kidney cells affected by the disease. They discovered that when the gene for the protein called Polycystin 2 is turned off or missing, cellular energy ramps up, leading to the formation of cysts that damage the kidneys.

With this insight, the researchers have identified a promising approach for treating the condition by targeting the abnormal increase in kidney cell energy and growth. Having this novel target for drugs opens the door for developing new therapies that will benefit patients, they said.

The study, co-authored by Allison Brill working in Ehrlich’s lab, was published in Science Signaling.


From Science Signaling

Polycystin 2 regulates mitochondrial Ca2+ signaling, bioenergetics, and dynamics through mitofusin 2


PC2 separates mitochondria from the ER

Patients with loss-of-function mutations in polycystin (PC) 1 or 2 develop fluid-filled cysts due to excessive proliferation of kidney epithelial cells. Kuo et al. found that loss of the ER cation channel PC2 led to increased abundance of the mitochondrial fusion factor MFN2 and enhanced tethering of mitochondria to the ER. The increased mitochondria-ER association resulted in greater mitochondrial Ca2+ influx, biogenesis, and respiration and cellular proliferation, which in cultured cells and mouse models of polycystic kidney disease was rescued by deficiency in MFN2. These results show that PC2 acts to restrict mitochondrial tethering to the ER in kidney cells to prevent inappropriate Ca2+-dependent increases in mitochondrial function and cellular proliferation.

Abstract

Mitochondria and the endoplasmic reticulum (ER) have an intimate functional relationship due to tethering proteins that bring their membranes in close (~30 nm) apposition. One function of this interorganellar junction is to increase the efficiency of Ca2+ transfer into mitochondria, thus stimulating mitochondrial respiration. Here, we showed that the ER cation-permeant channel polycystin 2 (PC2) functions to reduce mitochondria-ER contacts. In cell culture models, PC2 knockdown led to a 50% increase in mitofusin 2 (MFN2) expression, an outer mitochondrial membrane GTPase. Live-cell super-resolution and electron microscopy analyses revealed enhanced MFN2-dependent tethering between the ER and mitochondria in PC2 knockdown cells. PC2 knockdown also led to increased ER-mediated mitochondrial Ca2+signaling, bioenergetic activation, and mitochondrial density. Mutation or deletion of the gene encoding for PC2 results in autosomal dominant polycystic kidney disease (ADPKD), a condition characterized by numerous fluid-filled cysts. In cell culture models and mice with kidney-specific PC2 knockout, knockdown of MFN2 rescued defective mitochondrial Ca2+transfer and diminished cell proliferation in kidney cysts. Consistent with these results, cyst-lining epithelial cells from human ADPKD kidneys had a twofold increase in mitochondria and MFN2 expression. Our data suggest that PC2 normally serves to limit key mitochondrial proteins at the ER-mitochondrial interface and acts as a checkpoint for mitochondrial biogenesis and bioenergetics. Loss of this regulation may contribute to the increased oxidative metabolism and aberrant cell proliferation typical of kidney cysts in ADPKD.


Living with PKD

From Post-Journal, Jamestown, NY, by JORDAN PATTERSON


Regaining Life  Falconer Resident In Need Of Kidney Donation



Ginger Blair-Farmer, pictured with her family, is in need of a kidney. The Falconer resident, in association with The Kidney Connection, is searching for a donor within the surrounding community.

Ginger Blair-Farmer just wants her normal life back.

Diagnosed with polycystic kidney disease, Blair-Farmer is scheduled to begin dialysis treatment if a donor fails to come forward before her kidney essentially shuts down.

“I would be getting back life,” she said of receiving a transplant. “I’d be getting back a life, a quality of life that I wouldn’t be able to have without a kidney donor.”

At the time she spoke to The Post-Journal, her kidney was functioning at 14 percent. She expects that within six months she will her kidney will need the dialysis treatment as functionality will have reached a critical percentage.

While dialysis is a viable option, she hopes a donor will come forward soon.

The Kidney Connection, a locally managed curator of donors, is again asking for the community’s help to provide Blair-Farmer with an organ she desperately needs.

Currently, she is on two transplant lists, but maintained the chances of finding a successful donor increases as she continues to promote herself. A main reason she reached out to The Kidney Connection was to simply do something rather than “do nothing.”

Blair-Farmer is the mother of five children. Diagnosed with polycystic kidney disease at the age of 21, it slowly began shutting down her kidney. Over the last four years, she said her kidney’s decline as increased more rapidly.

Blair-Farmer will soon turn 43 and hopes that a potential transplant can be organized this year. Her father, who was diagnosed with the same disease, had his first transplant at 44.

Now with hopes of getting a transplant of her own around the same age when her father underwent the same process, her oldest daughter, Gabrielle Blair, was recently diagnosed with the kidney-deteriorating disease.

“She’s close to the age I was when I found out and my dad was going through it,” Blair-Farmer said.” “Now she knows and I’m going through it.”

While she understands what her daughter is going through, her hope is to receive a kidney transplant to allow her to become a fully-functioning member of her family again.

The disease, especially in the last few years, generally makes her fatigued much easier than normal. Blair-Farmer, an avid hiker, runner and cyclist said the sickness has taken much of what she loves away from her.

If she does, in fact, find a donor, she looks forward to, “just being a fun mom and not having life revolve around (her).”

“I want to be a part of the family instead of being a part of the family from the background,” she said.

Asked what she would tell potential donors, Blair-Farmer said interested individuals should visit The Kidney Connection website.

Even if people decide to not donate to her specifically, she encouraged people to browse the sight to possibly donate to the other individuals on the site as some people have been waiting “a really long time.”

For anyone considering donating an organ, she said, “the difference you make in someone else’s life is tremendous. It’s a small sacrifice but comes with big changes for other person.”

Blair-Farmer’s story, as well as others, can be found at kidneyconnection.org.


From Cleveland Clinic

5 Kidney Failure Symptoms to See Your Doctor About

Plus, two easy-to-spot kidney disease risk factors

Your kidneys are like the technical crew from the latest “Avengers” movie. They may not be the flashy superheroes, but without their unsung work, you don’t have a blockbuster.

Your kidneys have the thankless but critical job of getting rid of waste and extra fluid. Plus, they keep your organs working. Nephrologist Juan Calle, MD, explains how to look for early signs of kidney disease so you can keep your kidney crew as healthy as possible.
When kidneys aren’t doing their jobs

Renal failure, also called kidney failure or kidney disease, happens when the kidneys are not working efficiently or effectively. An estimated 37 million U.S. adults are living with chronic kidney disease, according to the U.S. Centers for Disease Control and Prevention.

Even more shocking? Nine in ten adults who have it don’t even know it.

How could that be? “People don’t usually have noticeable signs of kidney failure until it is very advanced,” says Dr. Calle.


This sneak attack is why kidney failure is known as a “silent killer.”

By the time it’s diagnosed, dialysis and kidney transplant usually have unwelcome seats at the table. So it’s critical to catch any problems before kidney dysfunction passes the point of no return.
Get to know the signs of kidney failure

So how do you turn up the volume on this silent killer? Dr. Calle says to pay attention to these five signs of kidney failure:

1. High blood pressure: Kidneys help regulate blood pressure by releasing hormones. When they are damaged, they can’t do their job effectively.

2. Changes in your urination habits: You may be urinating less frequently or not at all. Your urine may appear frothy or darker (think the color of tea or cola). “Even a little blood can change the color of urine dramatically.”

3. Swelling, or edema: This goes beyond the bloating some of us experience after a salty meal. “The swelling can happen anywhere. But people usually notice it more in their legs, lower back, face and eyelids.”

4. Nausea, vomiting and a decreased appetite: Too much waste in your body affects everything, including your stomach.

5. Brain fog: Excess waste can make it hard to concentrate. Your brain may feel “fuzzy.” You may also have less energy and feel unsteady or light-headed.

But here’s the problem (as if we didn’t just list five): These symptoms seem to appear with no rhyme or reason. “You could have all the symptoms at the same time or intermittently, or you may have one but not the others,” Dr. Calle explains. It can feel like playing symptom Russian roulette.

To play it safe, see your doctor even if just one of these symptoms makes an appearance.
Watch out for these two risk factors

Two risk factors may rear their ugly heads before you notice any kidney failure symptoms, giving you a head start to get on top of this disease.

The first one to watch for is high blood pressure (again). “High blood pressure may be a sign of kidney disease, or it may cause it. It’s the chicken-or-egg dilemma,” Dr. Calle says.

Diabetes is another key risk factor. “Anyone who has high blood pressure and diabetes needs to be screened for kidney diseases.”

Other important risk factors include:
Family history of kidney disease
Regularly taking nonsteroidal anti-inflammatory drugs (NSAIDs) such as aspirin, ibuprofen and naproxen as well as proton pump inhibitors (PPIs) such as omeprazole (Prilosec OTC®) that treat reflux and other GI issues
A past acute kidney injury, which is when your kidneys are damaged or fail suddenly
Certain chemotherapy regimens

And when in doubt, check it out. Dr. Calle recommends taking any questions or concerns to a primary care physician, internist or nephrologist.

“Don’t rely on your Internet research,” he says. “Some websites are not reputable and can needlessly scare you.”


From Renal and Urology News

Most Common ADPKD Imaging Modality Is Computed Tomography

adpkd-polycystic-kidney-disease-0416

Nearly half of patients with autosomal dominant polycystic kidney disease receive at least 1 CT scan over 2 years, study finds.


Investigators who studied a national sample of patients with autosomal dominant polycystic kidney disease (ADPKD) found that computed tomography (CT) was the most common imaging modality.

Nearly half of patients received at least 1 abdominal CT scan over 2 years, Myrlene Sanon, MPH, of Otsuka Pharmaceutical Development & Commercialization, Inc., of Princeton, New Jersey, and colleagues reported in a poster presentation.

Sanon’s team used the IBM MarketScan Commercial and Medicare Supplemental databases to identify patients with ADPKD. A total of 4637 patients with a mean age of 51.2 years met study enrollment criteria. The mean follow-up time was 21.29 months. During the observation period, 46.5% of patients had CT scans, 25.06% had ultrasound examinations, and 9.79% underwent magnetic resonance imaging, according to the investigators.

Of the 37.8% of patients who had information on chronic kidney disease (CKD) stage, the frequency of CT imaging was higher among those with later stage (31%, 37%, 42%, 51%, and 69% of those with stage 1, 2, 3, 4, and 5 CKD, respectively.

Overall, 12.9% of patients had a scan during an emergency department (ED) visit leading to hospitalization and 28% had a scan during an ED visit without subsequent hospital admission. In addition, results showed that without a prior ED visit, 30.7% of patients had a scan during inpatient hospitalization and 51% had scans as outpatients.

Read more of Renal & Urology News’ coverage of NKF’s 2019 Spring Clinical Meetings by visiting the conference page.

Sunday, May 5, 2019

KidneyX Awards: Wearable Dialysis and More, PKD Research: Octreotide-LAR, PKD Foundation Award, PKD Discrimination Lawsuit Settled

Kidney Dialysis

From University of Washington Medicine Newsroom

Contest award validates ideas for wearable kidney dialysis

conceptual illustration of the wearable dialysis unit


A conceptual illustration of the wearable dialysis unit being developed by the CDI.


In 2014, Chuck Lee of Bothell, Washington, was among seven subjects in a clinical trial of a “Wearable Artificial Kidney.” The proof-of-concept dialysis device was an exciting idea for patients like Lee who have irreversible kidney failure and whose survival depends on thrice-weekly clinic visits to be tethered to a large blood-cleansing machine for four or five hours.

At 11 pounds, the prototype trial device was clunky, and it had technical challenges. But Lee loved it because it allowed him to consume tomato juice, Cheetos and other favorites long gone from his diet, and it gave him freedom to walk around the hospital unit as dialysis took place.

The device represented the first significant innovation for those patients since the 1960s, when the University of Washington pioneered dialysis as a life-sustaining therapy.

Eager to pursue the idea of wearable dialysis, the UW Center for Dialysis Innovation (CDI) launched in 2017. It’s composed of doctors and engineers who are rethinking the dialysis circuit and hoping to make wearable dialysis a reality for kidney-failure patients.

Today the CDI was honored as two of its ideas were chosen as finalists in the KidneyX Redesign Dialysis competition, a national contest. Contest sponsors are the U.S. Department of Health and Human Services and the American Society of Nephrology.

“We’re excited to be recognized. It was competitive – over 160 submissions, from which 16 were selected,” said Kassandra Thomson, who directs the CDI’s efforts to translate research into clinical practice. Today she is in Washington, DC, presenting concepts along with other contest honorees.

Today’s winners are invited to develop their ideas into prototypes and to compete in the second phase of the competition, in which up to three winners will be awarded $500,000 each next year.

Thomson described the CDI’s two submissions. One described the vision for a next-generation wearable dialyzer, depicted as a compact device that will allow patients to receive dialysis 24/7. It will be water-efficient, enable complication-free blood access, and more fully model kidney function. Mostly, the device would afford mobility and allow patients to live lives more fully.

The other submission is a new vascular access graft. Blood-vessel access has been called the Achilles’ heel of hemodialysis. Current vascular-access technologies have a finite lifespan; patients suffer repeated needle sticks and, after many repetitions, the points of access can fail and complications can ensue.

“The new arteriovenous (AV) graft we are designing will be resistant to repeated needle punctures, reduce blood clots that might form inside the graft, and induce blood vessels to grow into the graft, so that it becomes more like a piece of living tissue," Thomson said. “The goal is to dramatically improve outcomes and the patient experience with their vascular access, addressing unsolved problems that have plagued patients for decades."

Kidney disease has become a staggering health burden in the United States, affecting 40 million people. More than 700,000 of them have kidney failure, which means being on dialysis, getting a transplant, or dying.

“It’s time for the next big advance,” Thomson said, “and we want it to happen here.”

WASHINGTON — HHS awarded more than $1 million in prize money last week during its first KidneyX Summit. Here is a summary of the recipients and their projects.


Vascular access

Researchers/Developers: Mohammad R. Haider, PhD, and Steven D. Gardner

Department of electrical and computer engineering, The University of Alabama at Birmingham

Device: A non-invasive, wearable telehealth device to detect thrombosis and monitor the health of arteriovenous fistulas and grafts in patients on hemodialysis. It uses a small sensor to monitor the patient’s vascular access in real time and sends the acquired data to a local microcontroller for signal processing. A machine learning algorithm then classifies the input data to identify hemodialysis vascular access clotting and automatically alerts patients and their health care teams.

Researchers/Developers: Dimitri Augustin, MD

Stanford University Nephrology fellow and Stanford Biodesign alumnus

Racquel Redwood Meng

Stanford Biodesign alumnus

Device: A wearable, real-time monitor of arteriovenous fistula attributes that identifies failing or properly maturing arteriovenous fistulas. Patients will benefit from real-time arteriovenous fistula data immediately postoperatively without requiring significant time, skills of a health care professional or concurrent connection to a hemodialysis machine. When early arteriovenous fistula maturation failures are identified, providers will be notified in order to evaluate if early interventions are necessary.

Researchers/Developers: Access for Life Inc., Daniel Nadis, Roger Mason, MD

Device: This smart sensor-enhanced needle guide is implanted in the subcutaneous tissue. It directs a blunt needle through an opening in the skin to an underlying fistula, reducing pain from large bore needles. A biosensor on the JEM cylinder with an audio-visual alarm will reduce risks of back wall perforation and needle dislodgement. The sensors also measure blood flow, allowing nephrologists to identify increased stenosis risk.

Researchers/Developers: Yael Vin, MD, MPH, FACS; and Matthew Phaneuf

Beth Israel Deaconess Medical Center in Boston

BioSurfaces LLC in Ashland, Mass.

Device: Beth Israel and BioSurfaces LLC are developing a drug-eluting electrospun hemodialysis graft. “We have the technology to incorporate drugs that reduce neointimal hyperplasia into the electrospun fibers and localize this attachment to a certain segment (venous edge) and layers of choice (inner layer, mid layer),” the researchers wrote.

Hemodialysis

Researchers/Developers: Outset Medical Inc. in San Jose, Calif.

Device: The proposed innovation provides for an integrated, automated means of monitoring of important physiological parameters during hemodialysis, including blood volume status (absolute and relative), vascular access function (flow rate and circulation) and ultrafiltration rate. “This is especially impactful in care settings such as in-home or in-center self-care hemodialysis, where patients take on greater ownership of their therapy,” the researchers wrote.

Researchers/Developers: Christian Schafmeister, PhD

Department of chemistry, College of Science and Technology, Temple University

Device: Schafmeister and colleagues are developing atomically precise membranes for high-flux and selective removal of blood toxins during hemodialysis. “We propose a solution to the problem of replicating kidney functions by creating chemically synthesized, atomically precise membranes that can be as thin as a single-molecule that mimic the highly permeable and selective membrane channels present in human cells,” Schafmeister wrote. “ ... This will open the door for renal replacement therapy to personalized/precise medicine beyond simple dialysis.”

Researchers/Developers: Peter Kotanko, MD; Stephan Thijssen, MD; Xia Tao, MD, PhD;

and Vaibhav Maheshwari, PhD

Renal Research Institute LLC in New York

Device: Kotanko and colleagues are developing a device to improve the intradialytic removal of protein-bound uremic toxins using binding competitors. Hemodialysis can remove uremic toxins, but protein-bound uremic toxins are the most difficult, the researchers wrote. They are infusing a displacer substance into the dialysis machine’s blood tubing upstream of the artificial kidney. The displacer binds to the same binding sites on albumin as the toxins. “Thus, it quite effectively competes with the toxins for their albumin binding, displaces them from the albumin molecule, and, once they are free, they can then be easily removed in the artificial kidney,” wrote the researchers. “In laboratory experiments, we have seen up to a three-fold increase in the removal rate of these toxins.” The plan with KidneyX funding is to develop an ideal displacer (or a combination of displacers) that can be used routinely in hemodialysis and study the impact on toxin removal.

Researchers/Developers: Ira Kurtz, MD, David Geffen School of Medicine at University of California, Los Angeles

Roland Ludlow, CEO and founder, Curion Research Corporation

Jamie Hestekin, MD, professor, department of chemical engineering, University of Arkansas

Device: The group is developing dialysate- and cell-free renal replacement technology that would not require the use of an external dialysate solution to drive the flux of ions and water across a membrane. The device couples multiple wafer electro deionization technology with pressure-driven ultrafiltration, nanofiltration and reverse osmosis modules specifically developed for this project.

CKD

Researchers/Developers: Kirby Binayao, RN, MBA; Karl Quint, MD; and Karen Naranjo

Renal Tracker, the Netherlands

Device: Renal Tracker delivers new or existing CKD self-management programs via digital platforms and uses behavior change elements to help patients modify progression risks.

Home dialysis

Researchers/Developers: Janelle Kaneda, Alisha Birk and Mark Buckup

Bioengineering department, Stanford University

Device: This device utilizes optical interrogation methods for early diagnosis of peritonitis.

The OpticLine will use spectrophotometry to analyze the optical density of whole blood counts (WBCs) in the dialysis waste fluid to gauge for infection. With a prototype, various WBC concentrations in Dulbecco’s phosphate-buffered saline were measured. “Our results from our works-like spectrophotometer prototype experiment indicate that we detect a significant difference in optical density between our two WBC concentrations of interest: 10 WBC/mm3 (normal) and 1,000 WBC/mm3 (infected) (P value = 1.47E-07),” the researchers wrote.

Infection control

Researchers/Developers: Alexander Yevzlin, MD

Director of interventional nephrology, division of nephrology

University of Michigan in Ann Arbor

Device: This is a nitric oxide-eluting, disposable hemodialysis catheter insert aimed at preventing infection and thrombosis. Nitric oxide (NO) is an endogenously formed gaseous molecule that is well known to play a key role in preventing infection and thrombosis. The disposable NO release insert will be replaced at each dialysis session (every 2 to 3 days).

Artificial kidney

Researchers/Developers: Shuvo Roy, PhD; William H. Fissell, MD; and Charles Blaha, MS

University of California, San Francisco; Vanderbilt University Medical Center in Nashville;

Silicon Kidney

Device: The researchers are developing a hemodialysis system (iHemo) that involves implanting a compact hemodialyzer (HemoCartridge) that creates a permanent internal vascular connection. “The iHemo will improve dialysis patient outcomes and their quality of life by eliminating risk of accidental blood disconnect and encouraging frequent and prolonged hemodialysis treatments, especially within the home setting,” they wrote.

Researchers/Developers: Jonathan Himmelfarb, MD; Buddy Ratner, PhD; Larry Kessler, ScD; Kassandra Thomson, PhD; Glenda V. Roberts; and Anna Galperin, PhD

University of Washington Center for Dialysis Innovation in Seattle

Device: The UW Center for Dialysis Innovation is developing the Ambulatory Kidney to Improve Vitality (AKTIV): a wearable, miniaturized dialysis system that “is low-cost, water-efficient, requires minimal anticoagulation, offers complication-free blood access and is patient-friendly,” the researchers wrote. “The AKTIV will provide sustained life, and higher quality, more productive lives for patients worldwide, allowing almost unlimited mobility, dramatically reduce pharmaceutical burden and reduce dietary restrictions.”

Researchers/Developers: Qidni Labs Inc.

Device: This is a project to develop an automatic air removal system that can be used safely in a wearable renal therapy device with minimal user intervention. This system uses an air removal filter of the design used in cardiopulmonary bypass and extracorporeal membrane oxygenation systems. This system can also determine and signal the patient with an alarm if the hydrophobic isolation filter element has been wetted and thus has reduced the accuracy of the integrated return blood pressure monitor.

Transplantation

Researchers/Developers: Jeff Ross; Joseph Uzarski

Miromatrix Medical Inc., Eden Prairie, Minn.

Device: Using multiple patented technologies, Miromatrix is working to bioengineer new kidney grafts that consist of human cells grown in pig extracellular matrix scaffolds. “Perfusion decellularization removes the native cells from pig kidneys while leaving behind a transplantable scaffold that provides the framework needed to grow a new kidney graft,” the developers wrote. Miromatrix’s perfusion software drives cells to regenerate kidney structures, including blood vessels and nephrons, in laboratory bioreactors. As an initial step, Miromatrix has developed a process to revascularize kidney grafts with consistent performance in vivo. Revascularized kidney grafts have shown sustained vascular patency on follow-up angiographies in chronic pig transplantation models without evidence of blood clotting.

Reference:

www.kidneyx.org/WhatWeDo/PrizeCompetitions/redesigndialysisphasei

In this randomized and placebo-controlled trial, researchers assessed the renoprotective effect of octreotide long-acting release (octreotide-LAR) in autosomal dominant polycystic kidney disease (ADPKD), the most frequent genetically determined renal disease, patients at high risk of ESRD due to later-stage ADPKD. For this investigation, 100 patients with estimated glomerular filtration rate (GFR) 15–40 ml/min/1.73 m2 were randomized to receive two 20-mg intramuscular injections of octreotide-LAR (n = 51) or sodium chloride (placebo; n = 49) every 28 days for 3 years. Investigators found that 3-year octreotide-LAR treatment did not significantly affect the decline in GFR vs placebo, but significantly slowed cyst growth and progression to end-stage kidney failure, especially in patients with more severe kidney failure (stage 4) to begin with, and was safe and well tolerated. Overall, the authors concluded that octreotide-LAR was well tolerated and during the study, there was no patient requiring interruption of treatment or even transient dose down-titration


Living with PKD

From JD Supra

Remedy Intelligent Staffing and Lornamead to Pay $50,000 to Settle EEOC Disability Discrimination Suit

Staffing Agency and Manufacturer Failed to Accommodate and Instead Fired Long-Term Temporary Worker With Kidney Condition, Agency Charged

BUFFALO, N.Y. - Remedy Intelligent Staffing, LLC, a California-based staffing firm, and Lornamead, Inc., a manufacturer headquartered in New York City, will pay $50,000 and furnish other relief to settle a disability discrimination lawsuit filed by the U.S. Equal Employment Opportunity Commission (EEOC), the federal agency announced today. The EEOC charged that Remedy and Lornamead violated federal law when they refused to provide a reasonable accommodation to a long-term temporary employee that would have enabled him to continue to work after his kidney condition worsened, and instead ended his employment.

According to the EEOC's suit, David Gaiser II was hired by Remedy and assigned to work as a general laborer at Lornamead's Tonawanda, N.Y., facility in June 2013. During his employment, Gaiser was diagnosed with autosomal dominant polycystic kidney disease, a chronic condition characterized by the growth of multiple cysts in the kidneys. In June 2016, Gaiser was assigned to run a machine that re­quired continual bending and twisting, which aggravated his kidney condition and caused him severe pain. Gaiser suggested several accommodations that could enable him to perform his job duties. Instead, Lornamead directed Remedy to end Gaiser's three-year assignment at Lornamead. Remedy failed to place Gaiser at another job with a different client.

Such alleged conduct violates the Americans with Disabilities Act (ADA), which prohibits discrimination based on disability and requires employers to provide a reasonable accommodation to individuals with disabilities. The EEOC filed suit (EEOC v. Lornamead, Inc. and Remedy Intelligent Staffing, Inc., Civil Action No. 1:18-cv- 00841) in U.S. District Court for the Western District of New York, Buffalo Division, after first attempting a pre-litigation settlement through the EEOC's conciliation process.

In addition to the $50,000 in monetary relief, the three-year consent decree settling the suit requires Lornamead to adopt new policies and procedures on disability discrimination and on providing accommodations to employees with disabilities. The decree also requires the company to train all supervisors, managers, and human resources personnel at the Tonawanda facility on Lornamead's obligations under the ADA. The company will also provide training to non-supervisory employees, including temporary employees placed by Remedy, on their rights under the ADA. Remedy will distribute its new policies explaining the ADA's prohibition against disability discrimination and Remedy's duty to provide reasonable accommodations to all employees and newly hired employees. Remedy will also provide training to all supervisors, managers, and human resources personnel responsible for temporary employees assigned to Lornamead's Tonawanda facility. The decree further subjects both employers to reporting, monitoring and record-keeping requirements.

"As joint employers, Remedy and Lornamead share a legal duty to provide reasonable accom­modations to people with disabilities," said Jeffrey Burstein, regional attorney for the EEOC's New York District Office. "We appreciate both employers' willingness to resolve this case without protracted litigation."

Kevin Berry, district director of the New York District Office, said, "The purpose of the ADA is to ensure equal employment opportunities to qualified people with disabilities. Firing a person because he or she needs an accommodation due to a disability is against the law, and the EEOC will continue to hold employers accountable."

Elizabeth Fox-Solomon was the EEOC's lead trial attorney for this case.

The EEOC's New York District Office is responsible for processing discrimination charges, administrative enforcement, and the conduct of agency litigation in Connecticut, Maine, Massachusetts, New Hampshire, New York, northern New Jersey, Rhode Island, and Vermont. The Buffalo Local Office conducted the investigation resulting in this lawsuit.


PKD Foundation

From healio.com

Researchers of polycystic kidney disease honored with Kaplan International Prize for Advancement


York Pei, MSc, MD, FRCPC, and Bradley Yoder, PhD, were presented with the Lillian Jean Kaplan International Prize for Advancement at the World Congress of Nephrology in Melbourne, Australia, according to a press release from the PKD Foundation.

The Lillian Jean Kaplan International Prize recognizes individuals whose scientific work results in improving the knowledge and treatment of polycystic kidney disease.


“It is my distinct honor to present both Pei and Yoder with the Lillian Jean Kaplan International Prize for their most significant research in the polycystic kidney field. And, we deeply appreciate Mr. Kaplan’s generous commitment in recognizing researchers in their quest to advance treatments for PKD,” Andy Betts, CEO of the PKD Foundation, said in the release. “The pioneering studies of these researchers provide great hope for the future for all PKD patients.”

According to the release, both researchers were awarded $50,000, a sculpture, a citation depicting their work and an opportunity to lecture during the World Congress of Nephrology about their research. Pei, a professor of medicine at the University of Toronto, focused on genetic, genomic, clinical and translational research and has made a significant contribution to advance diagnosis, prognosis and development of novel treatment in autosomal dominant polycystic kidney disease.

As professor and chair of the department of cell, developmental, and integrative biology at the University of Alabama at Birmingham Medical School, Yoder has spent 2 decades focused on understanding the function of the primary cilium in multiple tissues and during development, with a long-standing interest in how loss of cilia function contributes to cyst development in the kidney. His recent research has uncovered roles for primary cilia in regulating innate immune responses following renal injury that accelerates cyst progression.

Sunday, April 28, 2019

PKD Modeling with Kidney Organiods, Kidney Pain Signs, Medicare Rules Modification Could Lead to Dialysis Care Innovation, Kidney Delivery by Drone

Living with PKD

From Medical Daily, By Leian Naduma

Kidney Pain Signs, Symptoms And Causes

Renal or kidney pain is associated with several malfunctions of the organs or recurring infection. Sometimes, it is a mere urinary tract infection that can be remedied by lifestyle changes or prescription medication. Other times, it is a symptom of a serious mental condition. Here are the most common signs, symptoms and causes to help you identify if what you are going through is a mild or serious case of kidney pain.

Your kidneys are bean-shaped organs located on either side of your spine. They filter the blood and balance the number of fluids and electrolytes in your body. The level of pain you experience also depends on whether the cause is prerenal or related to another organ located near it, intrinsic or caused by the kidneys themselves or postrenal, which is typically due to an obstruction below the organs. Thus, the common triggers of kidney pain are an infection, obstruction, growth or trauma, as per VeryWell Health.

Trauma

Kidneys are placed at a vulnerable position in the abdomen which may easily be affected by a blunt force impact or a penetrating wound. If you have abdominal injuries, there is a 10 percent chance that you will also sustain damage to your kidneys. Events such as physical assaults and vehicular accidents result in renal trauma. You can distinguish this cause from others by pressing the kidney area and note a painful sensation. It may also be associated with fever, hematuria, urinary retention, rapid heart rate, decreased alertness and abdominal swelling. These symptoms require emergency treatment.

Renal Obstruction

This is a result of urinary blockage and it is an intrinsic type of kidney pain. The renal obstruction causes unilateral or bilateral pain due to affected ureters. This type of pain is also called obstructive uropathy which is caused by kidney stones, bladder stones, urinary tract infection, an enlarged prostate, pregnancy, long-term catheterization, a blood clot in the kidney, nerve-related bladder weakness, cancer, or vesicoureteral reflux. These cause your kidneys to swell and is referred to as hydronephrosis. You are most likely to experience pain in the groin, flak or abdominal area and may be associated with urinary urgency, fever, nausea and dysuria. Kidney stones cause higher pain levels while the others are gradual when left untreated.

Growth or Cysts

Renal tumors also cause pain and its intensity depends on the growth. The three most common growth abnormalities are renal adenoma, renal cell carcinoma and polycystic kidney disease (PKD). Larger ones do not cause pain until they disturb the architecture of the kidney. When this happens, the pain is persistent and worsens over time. If the tumor is cancerous, you may also experience unexplained weight loss, which suggests an advanced malignancy. PKD is also associated with headaches, high blood pressure, abdominal pain and swelling, hematuria and renal failure.

Infection

Kidney infection is treated with prescription antibiotics. This is caused by viral or fungal exposure that adversely affects the body’s immune system. Patients who have advanced HIV or underwent organ transplants are more vulnerable to this condition.

Prevention And Cure

As per Medicine.Net, most kidney pains can be relieved by drugs like ibuprofen, ketorolac and acetaminophen, which are common medications for pain. Antibiotics are recommended by doctors in infections while those who have kidney stones may need surgery.

Kidney pains caused by infections can be prevented by drinking sufficient amounts of water per day, wearing loose pants, following proper hygiene and refraining from holding your urine for long periods. Kidney stones and abdominal cancers, on the other hand, may be prevented by eating a healthy diet and avoiding salty and fatty foods.


From Health Care Finance, by Jeff Lagasse, Associate Editor

Modifications to Medicare rules could support care innovation for dialysis

Medicare spends approximately $35 billion annually on care for beneficiaries with end-stage renal disease.

In a commentary published in the American Journal of Kidney Diseases, public health researchers suggest adjustments to recently proposed rule changes on how Medicare pays for dialysis services.

Medicare spends approximately $35 billion annually on care for beneficiaries with end-stage renal disease, or kidney failure. That's more than 7 percent of Medicare's total paid claims. Over half a million people receive regular dialysis treatments to manage this condition, with treatment costs averaging about $85,000 a year, according to the study.

IMPACT

Rule changes were proposed about a year ago that would limit the number of dialysis treatments per week that would be paid for by Medicare. Interest groups including nephrologists and patients themselves were concerned that this would limit patient access to innovative treatment options, such as frequent hemodialysis.

Under the current system, Medicare covers three hemodialysis treatments weekly per patient, but it will often pay for additional treatments when the treating nephrologist provides sufficient medical justification.

The recently proposed rule changes would limit such additional payments to exceptional circumstances -- for example, patients with temporary, acute kidney treatment needs. Although nephrologists would not be prevented from providing any "extra" treatments they believe are needed, they would typically bear the costs of doing so.

The researchers discussed the limitations of the current evidence on frequent dialysis treatment, which to date has yielded mixed conclusions. Their suggested changes to Medicare's dialysis payment system were designed to account for these limitations and give Medicare the flexibility to further modify the system in the future as new evidence comes to light.

Under their main proposal, Medicare would establish a new, separate prospective payment system for frequent hemodialysis treatment.

In that way, they said, nephrologists would have greater clarity about how their dialysis care would be paid for, and free them up to pinpoint better ways to treat their patients.

THE TREND

In the first three years of Medicaid expansion due to the Affordable Care Act, the number of patients with end-stage kidney disease who died within a year of starting dialysis decreased in states that expanded Medicaid, compared to non-expansion states, found research published in October.

The adjusted absolute reduction in mortality in expansion states versus non-expansion states was 0.6 percentage points. Since end-stage renal disease affects more than 100,000 Americans each year, 0.6 percentage points equals hundreds of deaths annually.


PKD Research

Select Science

Modeling Kidney Disease with Bioengineered Kidney Organoids

 Dr. Benjamin Freedman, Assistant Professor at the University of Washington

Kidney organoid pioneer, Dr. Benjamin Freedman, explains the bioengineering, generation and application of 3D cell culture in studying kidney disease.

Kidney disease, prevalent in about 14% of the American population, lacks much-needed early interventions to prevent disease progression. Current methods that address kidney disease in a more chronic stage endure additional complexities: for example, artificial kidney devices don’t function as well as a human kidney, and renal transplant procedures need the support of anti-rejection medication.

In this article, we interview Dr. Benjamin Freedman, Assistant Professor at the University of Washington, whose goal is to understand kidney disease in its early stages. “In the medical practice, there's a lot of focus on the end stages of kidney disease and on managing that chronic disease. We are more interested in the early stages and all the different things that can go wrong early on,” says Freedman.

A pioneer in the field of kidney organoids, Freedman chose the 3D cell culture system to study kidney disease. “Organoids are great for this because they can show signs of disease,” Freedman explains. “We can then intervene by treating them with any compound that we're interested in.” A robust model for mimicking disease in vitro, kidney organoids didn’t even exist until a few years ago.

Freedman was the first scientist in the western hemisphere to generate a kidney organoid from pluripotent stem cells. “That was a very exciting moment,” Freedman recalls. “As soon as I saw these structures, I knew that there was something interesting about them. I had all the tools at my disposal to test whether they were indeed kidney.”

And they were.

Bioengineering kidney organoids

Developing and maintaining kidney organoids requires bioengineering capabilities. While the organoids grow and self-assemble from stem cells, their in vitro development deprives them of the vascular perfusion otherwise available in vivo. Tiny microfluidic tubules pass through the kidneys in our bodies, enabling the inlet and outlet of fluid, a resource that kidney organoids grown on a dish don’t receive.

“The kidneys in the body get about 20–25% of the cardiac output at any time point,” explains Freedman. “One thing we're missing in an organoid structure is the ability to perfuse the organoids and the tiny tubules.”

Freedman’s lab has a solution to this problem. “We're trying to make the kidney organoid 2.0, which will incorporate not just the stem cells and their natural ability to form the structures but will also impose a bioengineering design on top of those structures to enable them to really form the very complex types of functional tubules that are found in the body.”

Kidney Organoids in the Freedman lab
Kidney organoids cultured in the Freedman lab. Images from left to right; blood vessels joining kidney organoids; grown from reprogrammed skin cells; showing cyst growth from tubules; kidney podocytes. Image courtesy of the Freedman lab.

Mimicking in vivo environments

The kidney organoid 2.0 grows on a kidney-on-a-chip device incorporated with extracellular matrix in scaffolded arrangements. By seeding the stem cell-derived kidney cells on this matrix-coated chip, the cells can be grown into controlled shapes and arrangements. “It's a fusion between stem cell and bioengineering fields,” explains Freedman. “The chip, about the size of a credit card, has a tiny tubule structure through which we can perfuse liquid. We can then observe the absorption of solutes such as glucose and ions and see how they're transported from one side of the tubule to the other side.”

The procedure to generate organoids uses a thin layer of Corning® Matrigel® matrix at the bottom of the tissue culture dish. The cells are plated on top of this layer, followed by a second thin layer of Matrigel. “This enables the cells to fold up and create more three-dimensional types of structures which are about 200 microns in diameter,” says Freedman. “These contain all the key lineages of the kidney tissue that we're interested in.”

The Matrigel matrix forms a crucial component of the kidney organoid generation process from pluripotent stem cells. “Matrigel matrix helps the cells to survive. They need a malleable support that they can grow into and form more three-dimensional structures in; something that they can actually change and remodel as they're growing,” Freedman explains.

For the kidney-on-a-chip protocol, the Freedman lab uses a relatively strong and stiff extracellular matrix. “We use Corning Collagen I, a highly concentrated form of collagen because these gels need to be stiff for the cells to take on the right shape that we’re interested in,” says Freedman. “If it’s too soft, the whole thing just falls apart, especially because we have fluid running through it.”

Alternatively, after the organoids have formed, they are placed inside larger Corning Collagen I droplets to stimulate the cells to grow out and populate. “This way, we study the ability of these cells to migrate out of the organoid, which has ramifications for certain disease processes,” says Freedman. “The tubular cells, which are normally sedentary, can actually migrate out when you give them an environment like that.”

Better detached than attached

One of the projects in the Freedman lab involves studying polycystic kidney disease using the kidney organoid model. “In polycystic kidney disease, the tubules, which are normally very narrow, swell up to form large balloon-life structures. They eventually crowd out and destroy all the healthy kidney tissue,” explains Freedman. “We’ve been able to get this to actually happen in our kidney organoids by mutating a gene in the stem cells and derive organoids that are mutants. The organoids swell just like the kidney tubules in the disease.”

This swelling process, however, depends on the microenvironment the organoid finds itself in. Freedman adds: “If you grow the organoids in a condition where they’re essentially floating in media, then it accelerates and exacerbates the disease process.” The lab uses Corning ultra-low attachment plates to grow the organoids detached. “They make these big balloon-like cyst structures very well in the ultra-low attachment plates,” notes Freedman. “They don’t do as well when grown in normal tissue culture conditions.”
The next big thing for 3D cell culture

High-throughput chemical and genetic screening are soon making their way into 3D cell culture biology. “We’re going to move from a phase where we study one drug and its effects at a time to a stage where we’re interrogating the organoids with thousands of compounds,” says Freedman.

“This is something you can’t do in the mammalian animal model, so it’s an exciting time for unbiased discovery using organoids. The big data phase is upon us.”


Kidney Transplant News

From Yahoo Finance

Pioneering Breakthrough: Unmanned Aircraft Delivers Organ for Successful Kidney Transplant in Maryland


COLLEGE PARK and BALTIMORE, Md., April 26, 2019 /PRNewswire/ -- In a first-ever advancement in human medicine and aviation technology, a University of Maryland (UMD) unmanned aircraft has delivered a donor kidney to surgeons at the University of Maryland Medical Center (UMMC) in Baltimore for successful transplantation into a patient with kidney failure. This successful demonstration illustrates the potential of unmanned aircraft systems (UAS) for providing organ deliveries that, in many cases, could be faster, safer, and more widely available than traditional transport methods.

The momentous flight was a collaboration between aviation and engineering experts at the University of Maryland; transplant physicians and researchers at the University of Maryland School of Medicine (UMSOM) in Baltimore; and collaborators at the Living Legacy Foundation of Maryland.

"This whole thing is amazing. Years ago, this was not something that you would think about," said the kidney recipient, a 44-year-old Baltimore resident who spent eight years on dialysis before undergoing the transplant procedure.The patient was discharged from UMMC on Tuesday.

Maryland faculty and researchers believe this prototype organ transport blazes a trail for the use of UAS to expand access to donated organs, improving outcomes for more people in need of organ transplants.

"This history-making flight not only represents a breakthrough from a technological point of view, but provides an exemplary demonstration of how engineering expertise and ingenuity ultimately serve human needs—in this case, the need to improve the reliability and efficiency of organ delivery to hospitals conducting transplant surgery," said Darryll J. Pines, Ph.D., UMD, dean of the A. James Clark School of Engineering and Nariman Farvardin Professor of Aerospace Engineering. "As astonishing as this breakthrough is from a purely engineering point of view, there's a larger purpose at stake. It's ultimately not about the technology; it's about enhancing human life."

Added Joseph Scalea, MD, assistant professor of surgery at UMSOM, project lead, and one of the surgeons who performed the transplant at UMMC, "As a result of the outstanding collaboration among surgeons, engineers, the Federal Aviation Administration (FAA), organ procurement specialists, pilots, nurses, and, ultimately, the patient, we were able to make a pioneering breakthrough in transplantation."

The many technological firsts of this effort include: a specially designed, high-tech apparatus for maintaining and monitoring a viable human organ; a custom-built UAS with eight rotors and multiple powertrains to ensure consistently reliable performance, even in the case of a possible component failure; the use of a wireless "mesh" network to control the UAS, monitor aircraft status, and provide communications for the ground crew at multiple locations; and aircraft operating systems that combined best practices from both UAS and organ transport standards.

"We had to create a new system that was still within the regulatory structure of the FAA, but also capable of carrying the additional weight of the organ, cameras, and organ tracking, communications and safety systems over an urban, densely populated area—for a longer distance and with more endurance," said Matthew Scassero, MPA, director of UMD's UAS Test Site, part of the A. James Clark School of Engineering. "There's a tremendous amount of pressure knowing there's a person waiting for that organ, but it's also a special privilege to be a part of this critical mission."

Sunday, April 14, 2019

PKD: Vitamin D Kidney Failure Danger, Understanding PKD

Living with PKD

From Mount Sinai

Polycystic Kidney Disease

If one or both of your parents has been diagnosed with or carries the gene for polycystic kidney disease (PKD), you have a chance of developing the disease. It is one of the most common genetic diseases in the United States that can affect you at any age.

The severity of the disease depends on the number of cysts that grow in the kidneys, their size, and how much the growth of cysts interferes with kidney function. If you are experiencing kidney problems and a parent has the disease or genetic testing shows positive results, Mount Sinai's team of experts can help you.

Our team of highly ranked nephrologists has the expertise to diagnose, manage, and treat all forms of PKD. In addition, we have one of the leading research labs in the nation dedicated to studying people with PKD.

What Is PKD?

As its name indicates, polycystic kidney disease involves many cysts forming on and in the kidneys. Cysts are fluid-filled sacs that can grow larger and increase in number over time, causing the kidneys to become enlarged. The cysts are not cancerous, but as kidneys become enlarged and overrun with cysts, you may lose kidney function, leading eventually to kidney failure.

In some cases, cysts may also develop in the liver and other parts of the body, causing serious complications in the brain and heart. Another common complication of the disease is high blood pressure.

Types of PKD

The most common type, representing approximately 90 percent of all cases of inherited PKD, is autosomal dominant polycystic kidney disease (ADPKD). With ADPKD, if one parent has the disease, there is a 50 percent chance for each offspring to develop it, too. This form of the disease typically starts in adulthood, but can develop in childhood.

Another. much less common type of inherited PKD is autosomal recessive polycystic kidney disease (ARPKD). With ARPKD, two parents must carry the gene, and even then, there is only a 25 percent chance that each offspring will have it too. This form of the disease typically starts close to birth, but can occur later in childhood.

Symptoms

The following symptoms may indicate that you need to be examined and possibly diagnosed and treated for polycystic kidney disease:
Blood in the urine
Headaches
High blood pressure
Kidney stones and infections
Pain in the back or side
Swelling of the abdomen and feeling full
Urinary tract infections
Diagnosis

To diagnose cysts in the kidney, we may use various imaging tests: ultrasound, computed tomography scan, and magnetic resonance imaging. This also allows us to see how much of your healthy kidney remains functional.

Treatments We Offer

Once we have a clear picture of your kidneys, we can address your needs. We bring together specialists who tailor your care by using minimally invasive surgery to remove infected or bleeding cysts, medical genetics, urology, cardiology, pediatrics, and nutrition, all to help you. While there is no cure for PKD, we use highly advanced treatments and preventive therapies to relieve many of your symptoms.

Mount Sinai nephrologists and collaborating specialists employ a full range of medical and support services throughout the courses of your treatment. We pride ourselves in caring for our PKD patients with:

Continuity of care. At all ages and stages of the disease, our nephrologists work in close collaboration with pediatric nephrologists to transition your children with PKD from pediatric care to adult PKD care.

Genetic counseling. Our genetics department specializes in evaluating and counseling you and your family with a history of PKD.

Transplantation. We work closely with our transplant team and may suggest that you get an evaluation for a kidney transplant. Our Recanati/Miller Transplantation Institute surgeons and physicians, along with specialized nurses and social workers, coordinate care before and after kidney transplantation.

In addition to our Mount Sinai Health System community of clinicians and researchers, we consult with the New York chapter of the PKD Foundation. We attend annual PKD conferences and participate in the Walk for PKD.


From CMAJ Group, Canadian Medical Association Journal

Use of vitamin D drops leading to kidney failure in a 54-year-old man

KEY POINTS

Vitamin D toxicity is rare, but clinicians must be aware of the risks of vitamin D use to limit complications related to hypercalcemia.
Calcium levels may get worse before getting better in patients even after cessation of supplements, as vitamin D is fat soluble.

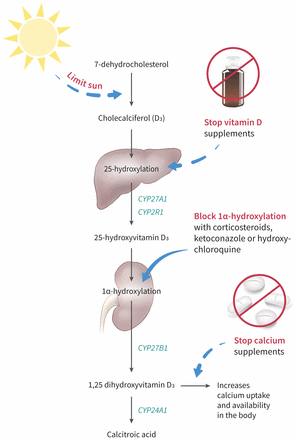
Observational data and expert opinion suggest that glucocorticoids, ketoconazole and hydroxychloroquine are reasonable options to treat hypercalcemia related to vitamin D toxicity by decreasing the “active” 1, 25 dihydroxyvitamin D3 levels.

A 54-year-old man was referred urgently to the nephrology clinic by his family physician for suspected acute kidney injury, with a creatinine level of 376 μmol/L. He had recently returned from a trip to Southeast Asia, where he had spent extensive periods sunbathing (6–8 h/d) for 2 weeks. His medical history included hypertension, dyslipidemia and gout, for which he was taking perindopril 8 mg daily, rosuvastatin 10 mg daily, amlodipine 10 mg daily, indapamide 2.5 mg daily and febuxostat 80 mg daily.

On his return to Canada, the patient’s creatinine level had initially increased from his baseline of 100 μmol/L to 132 μmol/L. His family physician instructed him to discontinue his antihypertensive and diuretic agents temporarily on the premise that he had possible extracellular fluid depletion from the heat exposure. Despite this measure, on repeat measurement 4 weeks later, the patient’s creatinine level had risen to 376 μmol/L. During this 4-week period, he had not used nonsteroidal antiinflammatory drugs or new medications, had not been exposed to intravenous contrast and had no acute illnesses. Given that his creatinine level continued to rise rapidly with no clear etiology, the patient was referred to nephrology.

The patient’s family history included autosomal dominant polycystic kidney disease, with 2 first-degree relatives requiring dialysis before age 60. However, he had undergone radiographic screening with abdominal ultrasonography, which was negative for polycystic kidneys.

At the nephrology clinic, the patient’s blood pressure was 149/98 mm Hg, with no urgent clinical indications for dialysis. Renal ultrasonography showed normal-sized kidneys with no hydronephrosis or echogenicity. An incidental 1.2 cm bladder mass was seen on ultrasonography and was later diagnosed as noninvasive urothelial carcinoma. (This was treated with local excision with interval surveillance, requiring no chemotherapy.)

Urine studies at the patient’s initial nephrology visit did not show leukocytes, erythrocytes or protein. There were no cellular casts or crystals seen on urine microscopy. Results of serum and urine protein electrophoresis studies were negative. Complete blood count was normal. However, the patient’s serum calcium and parathyroid hormone (PTH) levels showed a non-PTH-mediated hypercalcemia (Box 1). Testing of 25-hydroxyvitamin D3 and 1,25 dihydroxyvitamin D3 levels was ordered. Imaging studies of the chest and abdomen were unremarkable.

On more detailed questioning, the patient mentioned that he was seeing a naturopathic specialist who had prescribed high doses of vitamin D, advising him to take 8 drops of a specific brand daily. He did not have a history of a fragility fracture or documented vitamin D deficiency. The recommended brand contained 500 IU per drop. Unknowingly, the patient obtained another vitamin D preparation that contained 1000 IU per drop. The patient was not counselled about toxicity risks and, over a period of 2.5 years, he took 8–12 drops of vitamin D daily, for a total daily dose of 8000–12 000 IU.

At the nephrology clinic, the patient’s measured 1,25 dihydroxyvitamin D3 level was 274 pmol/L and his 25-hydroxyvitamin D3 level was 241 nmol/L (Box 1). He was instructed to stop taking all vitamin D supplements and calcium-rich foods. His diuretics remained on hold, but one of his antihypertensive agents (amlodipine) was resumed after his second clinic visit. His 1,25 dihydroxyvitamin D3 and ionized calcium levels continued to increase (Figure 2). His only new symptom related to hypercalcemia was pruritus.

Given his worsening hypercalcemia and increased active vitamin D levels, we counselled the patient about starting glucocorticoid therapy. He was reluctant to start glucocorticoids, given concerns about potential weight gain. As an alternative, we offered oral hydroxychloroquine at 400 mg daily and counselled the patient on adverse effects, including retinal toxicity.

The patient’s calcium and vitamin D levels decreased after initiation of hydroxychloroquine. Almost 1 year after diagnosis, his calcium and vitamin D levels have returned to normal, but he is left with stage 3B (estimated glomerular filtration rate 34 mL/min/1.73m3) chronic kidney disease.
Discussion

Historically, reports have outlined the benefits of vitamin D in relation to bone health.1 Other purported benefits of vitamin D included nonskeletal outcomes, such as cardiovascular benefit, fall prevention, and reduction of infections and malignancies.2 However, an umbrella review of systematic reviews and meta-analyses did not show that vitamin D reduces primary fracture risk or convincingly improves other nonskeletal health outcomes.3 Furthermore, a recent review for the US Preventive Services Task Force showed no benefit of vitamin D in preventing primary fracture in those without known deficiency, osteoporosis or prior fracture.4

In its 2010 guideline, Osteoporosis Canada recommended vitamin D supplementation of 10–25 μg (400–1000 IU) for most low-risk adults under the age of 50 years to achieve serum levels of 25-hydroxyvitamin D3 greater than 75 nmol/L (level 3 evidence),1 arguing that the potential benefits outweigh risks. A daily vitamin D intake of 20–50 μg (800–2000 IU) is recommended for high-risk and older adults (level 2 evidence).1

Mechanism of vitamin D toxicity

Although vitamin D toxicity is rare owing to a large therapeutic range, its widespread availability in various over-the-counter formulations may pose a substantial risk to uninformed patients. After consumption, vitamin D is carried to the liver where it undergoes hydroxylation and is activated by either microsomal CYP2R1 or mitochondrial CYP27A1 to 25-hydroxyvitamin D3.5,6 The resulting 25-hydroxyvitamin D3 binds to the vitamin D binding protein and is carried to the kidneys for further 1α-hydroxylation by CYP27B1 to produce 1,25 dihydroxyvitamin D3.6 This 1,25 dihydroxyvitamin D3 is transported to target cells and enters the nucleus of the vitamin D receptor, leading to an upregulation in gene expression. Although it is transported by vitamin D binding protein, 1,25 dihydroxyvitamin D3 has a lower affinity to binding relative to 25-hydroxyvitamin D3 and its metabolites.5 A leading hypothesis suggests that an oversaturation of the vitamin D binding protein causes an increase in free active Vitamin D (1,25 dihydroxyvitamin D3), resulting in hypercalcemia.

CYP24A1 plays an important role in the deactivation of 1,25 dihydroxyvitamin D3 to calcitroic acid.6CYP24A1 also breaks down precursor 25-hydroxyvitamin D3 to 24,25-dihydroxyvitamin D3. Loss-of-function mutations in CYP24A1 have been associated with hypercalcemia because of increased vitamin D sensitivity.6 Although we did not perform genetic testing on our patient, it is plausible that he had a CYP24A1 mutation, increasing his susceptibility to vitamin D toxicity.

Manifestations of toxicity

Toxicity can occur over a short period in patients ingesting large doses of vitamin D, either intentionally or inadvertently.7 The literature supports that doses greater than 10 000 IU per day for several months may lead to toxicity (> 200 nmol/L of 25-hydroxyvitamin D3).8 However, differences in patient characteristics such as malabsorption and mutations in CYP24A1 can lead to substantial variation in doses required for toxicity to occur.

Patients may present with symptoms involving the central nervous system and gastrointestinal, genitourinary and cardiovascular systems. Central nervous system manifestations include lethargy, hypotonia, hyporeflexia, confusion and coma. Gastrointestinal symptoms include nausea, vomiting, pancreatitis and constipation; cardiovascular symptoms of toxicity, such as hypertension, arrhythmias and QT segment shortening, may also occur.9 Genitourinary symptoms include polyuria, nephrocalcinosis and renal failure. The symptomatology associated with vitamin D toxicity underscores the suggestion that hypercalcemia may be responsible for most symptoms seen.7Sustained hypercalcemia can also lead to dysregulation of calcium–phosphate homeostasis leading to PTH suppression and impaired bone turnover.3,5

Importantly, patients may be asymptomatic, delaying diagnosis, and abnormalities related to vitamin D toxicity may be detected only incidentally.

In terms of renal involvement, hypercalcemia can cause kidney injury both acutely and chronically. Hypercalcemia can cause acute kidney injury primarily by 2 mechanisms: afferent arteriolar constriction and intravascular volume depletion from a diuretic effect through activation of calcium-sensing receptor at the sodium–chloride cotransporter in the loop of Henle.10 Our patient’s acute kidney injury was likely worsened by volume depletion from diuretic use, prolonged heat exposure and preexisting hypercalcemia from vitamin D toxicity. We saw some improvement in his renal function as his calcium levels decreased, by discontinuing his vitamin D supplements and temporarily holding his diuretics and antihypertensive agents. However, we believe that our patient developed chronic disease as shown by nephrosclerosis on renal biopsy (Figure 1).

Management of toxicity

In cases where vitamin D toxicity is suspected, patients should have their medications — prescribed and over-the-counter — carefully reviewed. Initial strategies to reduce vitamin D levels should focus on reducing dietary or supplementary sources. Although there is currently no evidence from large trials, observational data suggest that clinicians may consider strategies to reduce active vitamin D levels if hypercalcemia persists, through inhibition of 1α-hydroxylase activity (Figure 3).11,12 If patients are asymptomatic, clinicians may choose to monitor levels expectantly, as vitamin D is very fat soluble and levels may take some time to return to normal.
Figure 3:


Several medications have been used successfully to treat hypercalcemia by reducing the active form of vitamin D. Glucocorticoids, ketoconazole and hydroxychloroquine have all been used in cases of hypercalcemia related to sarcoidosis.1,9 Expert opinion suggests that these medications reduce 1α-hydroxylase activity and may be used to manage hypercalcemia by reducing 1,25 dihydroxyvitamin D3 levels.11,12 Given that our patient was reluctant to use glucocorticoid treatment, we used hydroxychloroquine as an alternative to decrease his 1,25 dihydroxyvitamin D3 levels and, in turn, his calcium levels.

Our experience informs us that patients and clinicians should be better informed about the risks regarding the unfettered use of vitamin D. Given new findings from the US Preventive Services Task Force,4 current Canadian guidelines regarding its use in low-risk individuals should be revisited.

Patients with CYP24A1 mutations may be at an increased risk of vitamin D toxicity, and clinicians can consider genetic testing if vitamin D toxicity develops with doses less than 10 000 IU per day. Although vitamin D toxicity is rare, early recognition may prevent chronic complications related to hypercalcemia. In patients who are symptomatic, cessation of supplements along with treatment with glucocorticoids is suggested. In cases where glucocorticoid therapy is not preferred or is contraindicated, ketoconazole or hydroxychloroquine are reasonable alternatives.

The section Cases presents brief case reports that convey clear, practical lessons. Preference is given to common presentations of important rare conditions, and important unusual presentations of common problems. Articles start with a case presentation (500 words maximum), and a discussion of the underlying condition follows (1000 words maximum). Visual elements (e.g., tables of the differential diagnosis, clinical features or diagnostic approach) are encouraged. Consent from patients for publication of their story is a necessity. See information for authors at www.cmaj.ca.

Sunday, April 7, 2019

PKD: Trying At Home Dialysis, Potassium Regulation in PKD, Update: CRISPR Gene Therapy

Living with PKD

From Fox News Channel 5, Atlanta

Kidney failure patient tries at-home dialysis


After 42 years of marriage, Roger and Raynelle Cash of Flowery Branch, Georgia, are not just husband and wife.

They are "care partners," working as a team to give Roger the kidney dialysis keeping the 62-year old alive.

Cash's kidneys failed in 2014, after a 20-year long battle with polycystic kidney disease.

"I was in pretty rough shape when I went into dialysis," he says. "So, even in the dialysis, I started feeling better, because they were taking the excess fluid off me."

At the time, Cash would go to a Fresenius Kidney Care dialysis center 3 days a week at 7 am.

There, he would spend up to 4 hours hooked to a machine filtering the toxins from his blood.

It was grueling.

"You feel pretty drained the days you have dialysis," he says. "And, in-center dialysis has a lot more variation, you feel good, feel real bad, feel good, feel real bad."

After his sessions, Cash would go to his job as a maintenance technician at a manufacturing plant.

But instead of feeling better, he started feeling more rundown.

"The longer I stayed on the in-center, daytime dialysis, the worst I felt," he says. "The weaker I got, the worse I felt."

So, Cash switched to an overnight, or nocturnal, dialysis center, thinking he could sleep through 8-hour sessions.

It didn't work.

"I was not sleeping in the center," he says. "I kept trying to work while I was nocturnal. Ultimately, it basically put me into a physical collapse."

He went on medical leave from his job and grew depressed.

That's when Fresenius Kidney Care offered the Cashes another option.

The company would train Roger and Raynelle to do his dialysis at home, using a machine called a dialyzer.

At first, his nephrologist at the time, Dr. Dinesh Chatoth, who is now the Associate Chief Medical Officer at Fresenius, says Cash was reluctant.

"His concerns were, number one, the machine looks pretty complicated," Chatoth remembers. "And, number two, how am I going to use these needles and stick myself in order to go on dialysis?"

Cash had a painful experience as a young boy when he says a nurse mistakenly gave him a penicillin shot in his arm.

It left him uncomfortable with needles, especially the idea of sticking himself.

But, he decided to try home hemodialysis.

"In all honesty I got desperate," Cash says. "Because I wanted to keep working,"

The Cashes went through 2 and half months of training at Fresenius, learning to set up, clean, and sterilize the machine.

They practiced sticking Roger with the needle.

When the time came for the real thing, Raynelle stuck Roger first, then he took over.

"It turned out to be quite a lot easier than I thought it would be."

Dr. Chatoth says the needles can be challenging for patients.

"There is phobia around that," Chatoth says. "But, once we can break through those barriers, once they experience better health, they tend to thrive and do better on dialysis at home."

Chatoth says Medicare and many insurance providers will pay for at-home dialysis for qualified patients.

He says it's less expensive to do the treatment at home, rather than in a center.

About 12 percent of Frensenius Kidney Care patients do at-home dialysis, Chatoth says.

Most, 10 percent do peritoneal dialysis, through a catheter in their belly.

Only 2 percent use the dialyzer for home hemodialysis, like Cash.

Cash sets his own hemodialysis schedule, 4 nights a week, 3 hours at a time.

He does it after work and before going to bed, in case he feels tired.

"Just about 2 and a half months into it, I woke up and said, 'You know, I feel a lot better,'" Cash says. "And, I felt better days and days in a row."

He and Raynelle have now been using the dialyzer for about 3 years.

Roger Cash has had a few bumps in the road, including a recent bout with colon cancer.

But, he says he's feeling good, and back at work.

"I am not as fast as I used to be, and I'm not as strong as I used to be," Cash says. "Don't have the stamina I used to have, but I can still get the job done. That meant a lot to me."


From Renal and Urology News, by Natasha Persaud

Hyperkalemia Less Likely in PKD Patients


Potassium regulation appears to differ in patients with polycystic kidney disease (PKD) compared with other etiologies of chronic kidney disease (CKD), according to the authors of a new study.

In an analysis of 1788 patients from the KNOW-CKD study (KoreaN cohort study for Outcome in patients With Chronic Kidney Disease), patients with PKD had significantly lower serum potassium levels and lower risks for hyperkalemia than other CKD etiologies during CKD stages 1 to 3b. Hyperkalemia prevalence was also lower among the 293 PKD patients than the other CKD groups up to CKD stage 3 to 4. In adjusted analyses, the risk for hyperkalemia was 5 times higher with diabetic nephropathy, 3 times higher with hypertensive nephrosclerosis, and twice as high with glomerulonephritis, than with PKD.

“Taking these results together, it can be suggested that patients with PKD may have a lower risk of hyperkalemia than those with other etiologies of CKD,” Hyoungnae Kim, MD, of Yonsei University in Seoul, and colleagues stated in BMC Nephrology. They added that further use of dual renin-angiotensin-aldosterone system (RAAS) inhibition may be beneficial in decreasing high intrarenal RAAS activity with a low risk of hyperkalemia in patients with PKD.

The team investigated renal potassium handling by measuring urinary angiotensinogen (AGT), a marker of intrarenal RAAS activity. In multivariable linear regression analysis, having a higher urinary AGT to creatinine (Cr) ratio correlated with lower serum potassium. The ratio appeared significantly higher in PKD patients than in other CKD patients. PKD patients also had a significantly higher transtubular potassium gradient (of urinary to serum potassium) that correlated with the AGT to Cr ratio. In PKD patients, a high urinary AGT to Cr ratio was associated with significantly increased risks for kidney function decline and all-cause mortality by 29%.

“In our study, we also showed that urinary AGT/Cr ratio was correlated with decline in renal function and mortality in patients with PKD. To our knowledge, this is the first longitudinal study that has shown urinary AGT as a prognostic marker in patients with PKD,” Dr Kim and his collaborators stated. The researchers acknowledged that the urinary AGT to Cr ratio can be increased with proteinuria, so additional studies are warranted.


PKD Research

From GEN, Genetic Engineering & Biotechnology News, By MaryAnn Labant

CRISPR Jump-Starts Gene Therapy

Instead of executing extensive overhauls, genomic mechanics are using CRISPR tools to make only the most targeted—and safest—repairs


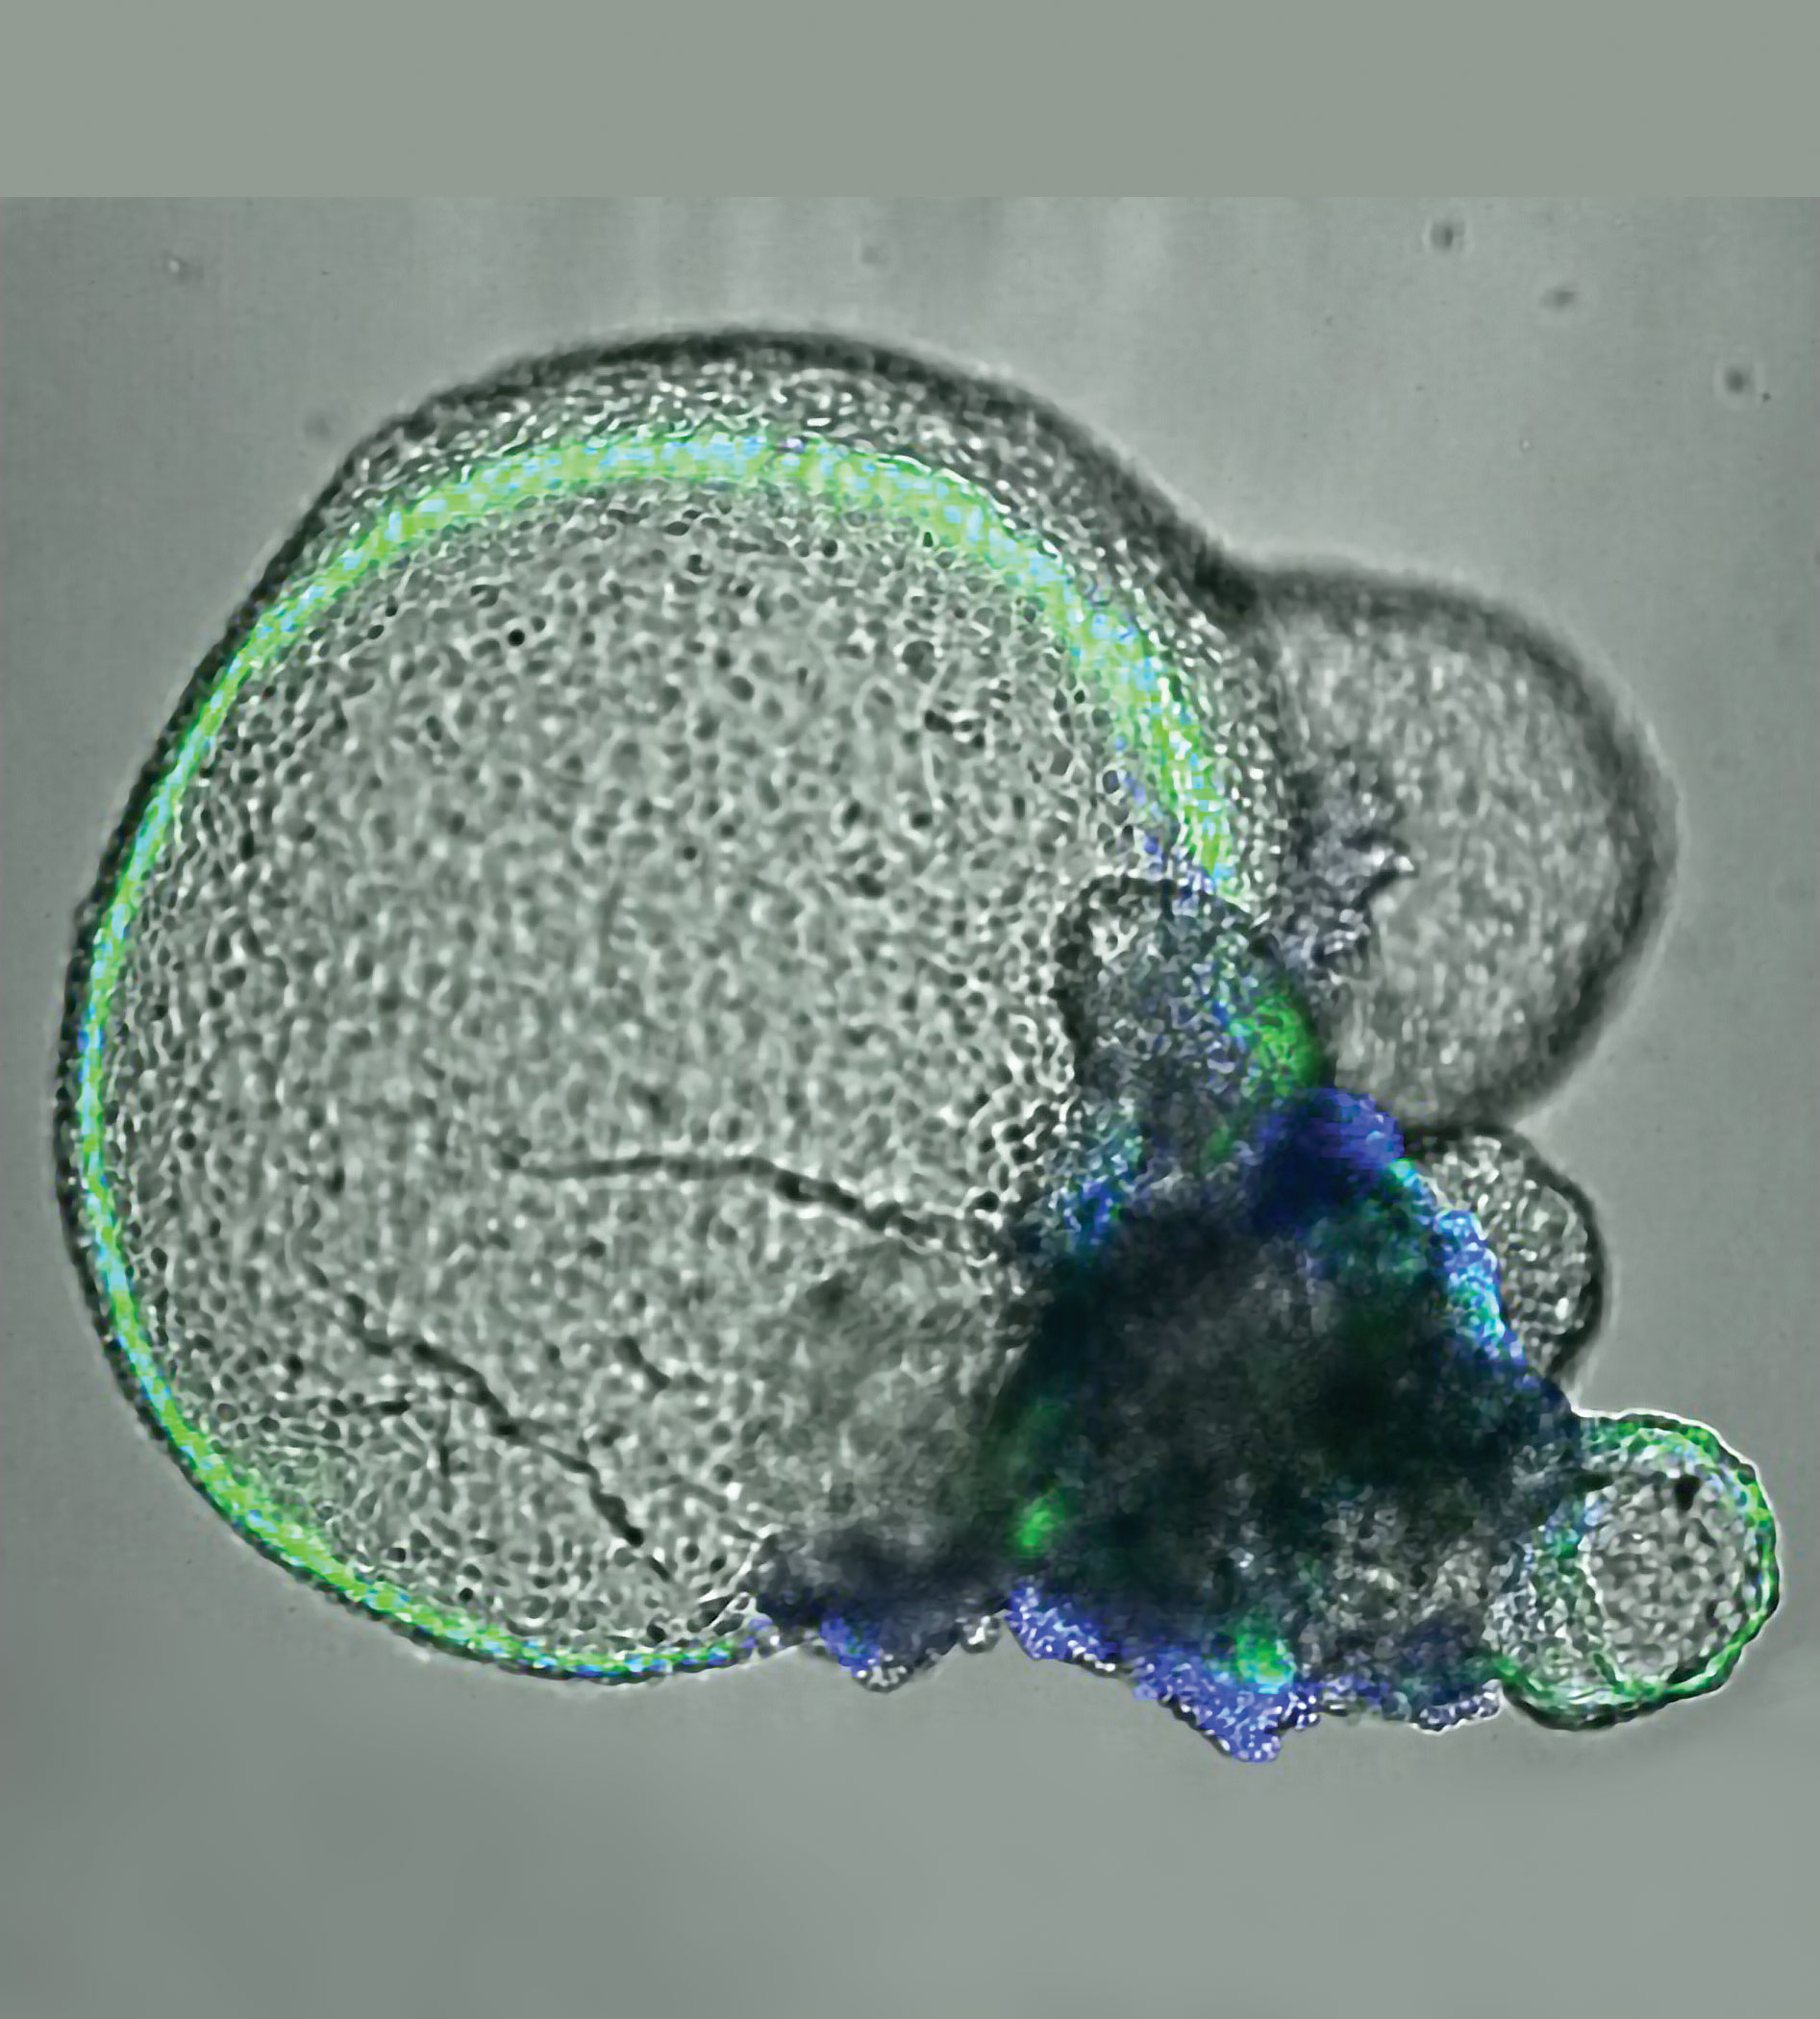
At the University of Washington, Benjamin “Beno” Freeman, PhD, and colleagues are using CRISPR gene editing technology to establish “disease-in-a-dish” models such as this 3D kidney organoid, which shows signs of polycystic kidney disease.


Gene therapy, like a car with mechanical problems, has a history of jerking to life and then quickly stalling. Fortunately, gene therapy has the benefit of a kind of roadside assistance, one that comes in the form of gene editing technology, which is becoming more precise. It can help gene therapy run more smoothly. For example, gene editing can now be used to silence or repair a faulty gene, rather than insert an entire gene into the genome. (If a replacement gene is poorly placed, it can cause insertional mutagenesis.) Several forms of high-precision gene editing can give gene therapy a jump, but the most electrifying form is probably CRISPR.

CRISPR is relatively affordable and easy to use. Consequently, it is being embraced by researchers, who are enthusiastically tinkering with CRISPR system components and developing CRISPR systems that are more efficient—and versatile.

Besides dissecting normal and pathogenic pathways, uncovering biomarkers, and identifying drug targets, CRISPR is starting to translate into the clinic. In February 2019, CRISPR Therapeutics and Vertex Pharmaceuticals achieved a major landmark by announcing the first dosing of a patient with a CRISPR-Cas9 therapeutic in a Phase I/II trial. The therapeutic, CTX001, is being used to treat patients with β-thalassemia. Later this year, the trial will be extended to include patients with sickle-cell anemia.

Other CRISPR biotech companies, notably Editas Medicine and Intellia Therapeutics, are also entering the clinic. These companies, which are focused on gene editing therapies for diseases of the eye and liver, share with Sangamo Therapeutics, Cellectis, and Bluebird Bio an interest in developing earlier forms of gene editing technology. These companies are relying on tools such as zinc finger nucleases (ZFNs), transcription activator-like effector nucleases (TALENs), and meganuclease–TAL effector fusions (megaTALs).

Although the older forms of gene editing technology are still relevant, the relative ease of use and affordability of CRISPR-Cas9 suggests that CRISPR will swiftly prove the most abundant platform for gene therapy. Investigators at Exonics Therapeutics recently reported very promising preclinical data using CRISPR gene editing for treating a canine model of Duchenne muscular dystrophy, in which genetic correction of the dystrophin gene appeared to restore limb function in affected King Charles spaniels, supporting advancement to the clinic.

Not only is CRISPR restarting gene therapy, it is also establishing a virtuous cycle of technological development. CRISPR has advantages that recommend it to a growing user base, which is working to enhance CRISPR strategies, methodologies, and nucleases, which keep broadening CRISPR’s appeal, and so on. This cycle may ultimately bring the benefits of gene therapy to patients, including patients suffering multigene disorders.

Mechanistic insights into kidney disease

The kidney is particularly challenging to study. The early stages of kidney disease are difficult to see, and patients with advanced stages of kidney disease often have secondary complications that affect disease understanding.

“There are many different forms of kidney disease, and there is no magic bullet to cure all of them,” says Benjamin “Beno” Freedman, PhD, assistant professor in the Department of Medicine at the University of Washington. “This is where precision medicine helps us to understand the root causes of disease and to intervene early, before dialysis or a transplant is required. Dialysis is crude compared to a functional organ and typically is not a long-term solution, and there is a lack of transplant organs.”

An experimental system must recapitulate some of the kidney’s complex composition and functions. The Freedman laboratory helped to develop the 3D kidney organoid technology that fulfills this need. Kidney organoids are made from stem cells; multiple cell types develop in a relatively intricate nephron-like arrangement that looks similar to the types of structures seen in the kidneys.

The geometry can differ depending on growth conditions, but all kidney organoids are essentially the same regardless of the laboratory of origin. Results are reproducible from laboratory to laboratory, lending standardization and credibility. Using single-cell RNA sequencing and other tools, researchers have found that organoids naturally make about 15 of the approximately 30 types of cells within the kidney.

“One of the very powerful aspects of CRISPR is that it is a functional tool,” Freedman emphasizes. “It changes an outcome and allows us to manipulate these organoids. This makes it possible to start interrogating and identifying the pathways that are involved in constructing the kidney in a functional way and to recreate disease in the organoids.”

Although there is a contribution of genetics to any form of kidney disease, 10–15% of kidney disease is caused by single-gene mutations. If these mutations could be corrected, a big dent would be made in the number of transplants needed. But CRISPR, while more efficient than other technologies, is still not 100% precise—off-target effects remain a concern to many investigators.

Polycystic kidney disease (PKD) is one of the most common genetic diseases, affecting 1 in 600 people. PKD has few treatments and no cure, making it a good candidate for a gene therapy approach. The genes that cause the disease are known, but it is not known how they normally work in the body.

Using the organoids and CRISPR, the Freedman laboratory has developed a PKD disease-in-a-dish model. The model is shedding light on how PKD occurs at the mechanistic level, leading toward finding interventions to halt disease progression.1

“We have also used CRISPR to produce kidney organoids with fluorescent proteins to better visualize how kidney cells work and the effects of treatments on these cells,” Freedman points out. “CRISPR is an excellent research tool because it allows us to investigate genetic pathways in a way that is far more specific than we were able to do before.”

An approach for monogenic blood disorders

Approximately 75% of all monogenic mutations are caused by point mutations—missense, nonsense, and frameshift mutations. Ideally, these disease genes should be corrected directly at their endogenous loci.

Homology-directed repair (HDR) has low repair efficiency. The dominant repair pathway in cells is usually non-homologous end joining (NHEJ). In theory, this repair mechanism should restore the open reading frame (ORF) that is disrupted by a particular disease mutation in approximately one third of the indels. NHEJ should lead to a significant number of ORF reconstitutions.

“My research results show a gene repair efficiency of up to 25% for some CYBB [cytochrome b-245 beta chain] mutations and an on-target mutation rate of 75% at the endogenous CYBB locus,” says Duran Sürün, PhD, a postdoc in medical systems biology at the Dresden University of Technology. “I am convinced that a donor-template-free, RNA-guided Cas9 endonuclease (RGN) approach has a high potential for personalized gene therapy of chronic granulomatous disease (CGD) and other monogenic blood disorders.”2

Although HDR can be utilized for its precise gene repair mechanism, the efficiency is low and requires a positive selection to enrich for gene-corrected cells. This low efficiency arises from double-strand break (DSB) repair in mammalian cells predominately occurring by NHEJ. More importantly, NHEJ represents the dominant DSB repair pathway in hematopoietic stem and progenitor cells (HSPCs).

Furthermore, the donor template required for HDR introduces a risk of random integration. For that reason, the donor-template-free RGN approach is a better strategy for the potential use in personalized gene therapy, Sürün believes.

Currently, the delivery of Cas9 into stem cells proves to be the greatest challenge. Ideally, RGN delivery for gene therapy should be transient and virus free to avoid insertional mutagenesis and immunological side effects. Special consideration should be given to alternative RGN delivery strategies for future experiments.

Advanced electroporation strategies are most promising. RGNs can be delivered as preassembled gRNA/Cas9 protein complexes. Next steps are to test this strategy in patient-specific HSPCs that will be transplanted after ex vivo gene repair into immunodeficient NSG mice.

Genome-editing tools open a wide range of new possibilities in gene manipulation including target-specific gene repair. The results of the first gene therapy studies in patients will be decisive for the further usage of the CRISPR-Cas9 system. According to Sürün, the new Cas9 protein versions hold great promise because they show less off-target activity in cells.

Merging expression levels with safety

CRISPR-Cas9 is a transformative tool that will continue to operate at the leading edge of basic and translational research. According to Mark J. Osborn, PhD, assistant professor, Department of Pediatrics at the University of Minnesota, a recent study3 had the goal of merging the expression levels achieved with lentiviral transgenesis with the safety of gene editing.

When a viral vector is used, it is common for multiple copies of the vector to deliver their payloads to individual cells. If these payloads include strong transcriptional elements, they can promote high-level, sustained gene expression. These elements, whether they are delivered by retro- or lentiviral vectors, often integrate into the genome with a bias for transcriptionally active regions, causing serious adverse events. In contrast, gene editing can result in precision targeting; however, the endogenous promoter may be comparatively weak, resulting in low-level gene expression.

The Minnesota team inserted a powerful transcriptional element upstream of an endogenous start codon to drive high levels of gene expression with defined integration via HDR. Any nuclease has the potential for off-target effects due to overlapping sequence homology at other genomic loci. To reduce the potential off-target effects, Osborn and colleagues decided to rely on proper targeting to drive expression of a selectable marker that aided in selecting for proper targeting events.

Osborn indicates that his team is further assessing its strategy by defining and mapping potential off-target sites. The hope is that the approach will streamline engineering and make high-level gene expression safer than when integrating vectors are employed.

Identifying off-target effects

Identifying unwanted off-target effects remains an essential requirement for clinical translation of genome editing. Unfortunately, a well-validated method that can reliably identify these events in vivo has been lacking.

Filling this void is a sensitive, unbiased, and generalizable strategy called VIVO (Verification of In Vivo Off-targets). Developed at the Massachusetts General Hospital laboratory of J. Keith Joung, MD, PhD, VIVO allows for the robust identification of genome-wide CRISPR-Cas off-target effects in vivo. VIVO was described in a 2018 Naturearticle,4 which demonstrated that CRISPR-Cas can induce substantial off-target mutations in vivo and that appropriately designed guide RNAs can direct efficient in vivo editing without inducing detectable off-target mutations.

The VIVO approach can be used irrespective of the delivery method for CRISPR-Cas. It is envisioned as a two-step strategy: The first in vitro step uses the CIRCLE-seq method to identify potential off-target cleavage sites of a nuclease of interest on purified genomic DNA.5 Next, off-target sites identified by CIRCLE-seq are examined for evidence of indel mutations in the genomic DNA of target tissues in vivo that have been treated with the nuclease.

The in vivo detection limit of VIVO is limited by the current error rate of sequencing. Previous in vivo studies used computational in silico approaches or the GUIDE-seq method performed on surrogate cells in culture to identify off-target effects.

The results presented by Joung’s group provided the first convincing demonstration that CRISPR-Cas can induce significant off-target mutations in vivo, and, importantly, that these off-target effects can be eliminated with appropriately designed guide RNAs.